

The House Model of Care Teams
A Practice Guide for Effective Interprofessional Work
In the complex landscape of human services, no single professional can address the multifaceted challenges that clients face in isolation. The interconnected nature of human needs – spanning safety, emotional wellbeing, social connection, and material security – demands an equally interconnected response from service providers. Enter, the House Model of Care Teams: a framework designed to transform fragmented service delivery into cohesive, client-centred support systems. Whether you’re a seasoned professional or new to inter-professional work, this guide offers both conceptual understanding and actionable strategies to navigate the complexities of effective collaboration.
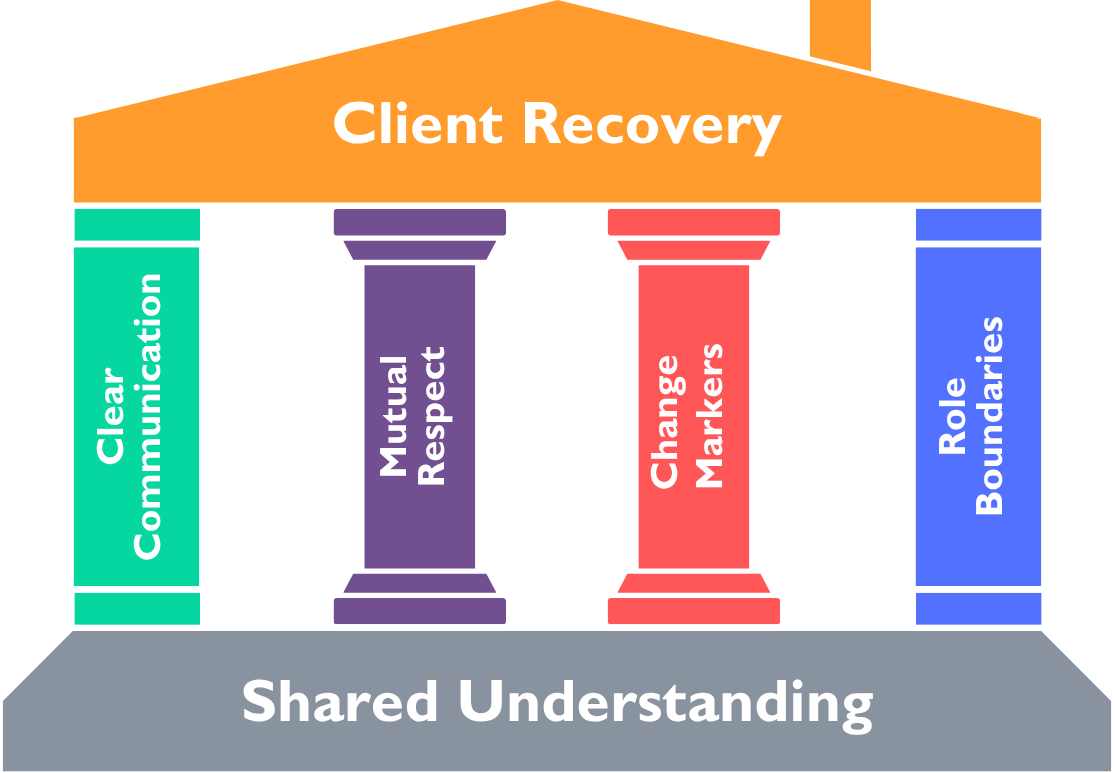
Inspired by Assoc Prof Michael Gordon’s ‘rules of good shared care’ and the Core Principles & Values of Effective Team-Based Health Care (Mitchell et al., 2012), this model is designed to be a teaching and practice tool across sectors. These ideas have been presented in a variety of contexts including as a talk at the Complex Needs Conference 2026.
The House Model of Care Teams is offered as a shared language and a practice framework for working together across professions and sectors. When an individual or family client's needs span several of safety, health, education, justice or disability, no single service can hold the whole picture. The House Model is designed to help teams move from parallel, fragmented efforts towards coordinated intervention that is coherent and effective even amidst complexity.
The model is based around the metaphor of building a house strong enough to shelter recovery, even when the client has multiple competing needs, repeating crises, or significant risk. Each element of the care team 'house' has a distinct function, and the structure holds together only when those elements reinforce one another.
A Shared Understanding is the foundation. As part of determining what the team will work on, it is imperative that an integrated picture of the client's story, strengths, and context is developed. Contributing to this is each professional’s partial view of the problem and the system around it. Bringing these together with the client's own voice allows the group's Shared Purpose to emerge: a specific though dynamic commitment to what success can look like and which needs come first in that. Without this base being firm, everything built above it can become unstable.
From this foundation, two walls rise to contain the work of the house. Clear Communication is the prices that integrates fragmented information into a coherent whole, through formal mechanisms (e.g. structured meetings, shared documentation, communication plans) as well as informal channels, flowing in both directions, including with the client. In the other side, Role Boundaries clarify who holds authority, responsibility and accountability for what. Boundaries that are both flexible and transparent prevent gaps or duplication and help make collaboration possible.
In routine casework, the foundation and those two walls are often sufficient to hold up a roof of collaborative recovery. However, as complexity increases, through experience of multiple traumas, recurring crises, or competing mandates, the roof presses down harder. Powerful relational dynamics can then pull practitioners from their roles, purpose and communication pathways, contributing to in effective work for clients in most need. When faced with this concern, two additional reinforcing struts become essential:
The first of these is Mutual Respect which creates the psychological safety for professionals to disagree productively, acknowledge uncertainty and repair ruptures – this is both critical to extend actively to the lived expertise of clients themselves as well as being an opportunity for professionals to model relational connection. Alongside this is using Change Markers to translate shared purpose into observable, jointly endorsed indicators of progress. These specific, observable steps toward change prevent case drift or stagnation, and build hope by making progress visible.
These five elements are interdependent and mutually supporting. When one weakens, the others come under greater pressure. When all are present and engaged, the care team can become an effective, trauma-informed system in which clients are active participants in planning and recovery. The model can also be used as a reflective tool. Introducing it to a care team invites a conversation around which parts of the house feel solid, and which need attention from us. Opening that conversation can reveal pressure points early, normalise the difficulty of complex work, and bring to the fore challenges which the practice tools here can support addressing.
From here, this guide presents each of the elements of the house in more depth. That is followed by a series of appendices providing practice tools to structure and reflection on your own care teams.
Elements of the House Model
-
A Care Team represents a purposeful alliance of professionals from diverse sectors who come together to support the wellbeing of their client – be it a child, adult, or entire family. Unlike formally established units within a single organization, these teams form organically yet deliberately, emerging as localized service intersections generated around an individual’s unique circumstances. They arise precisely because complex challenges rarely respect the boundaries of service silos; they spill across domains, requiring integrated responses.
The foundation of an effective care team lies in collective responsibility. Rather than working in parallel tracks, professionals pool their insights, resources, and authority to craft a cohesive plan tailored to the client’s specific situation. They maintain regular communication through structured meetings, shared documentation systems, or virtual check-ins, creating multiple opportunities to align their efforts, exchange critical updates, and collectively reflect on progress and setbacks.
-
The vision of seamless collaboration often collides with a much harsher reality on the ground. Instead of coordinated care, practitioners often find themselves navigating a maze of missed connections, conflicting priorities, and meetings that deteriorate into either accusatory finger-pointing or uncomfortable silence. Families bear the heaviest burden of this dysfunction, forced to navigate a bewildering patchwork of services while repeatedly recounting their stories to disconnected professionals who may never speak to one another.
Communication fractures under the weight of professional jargon, hierarchical dynamics, and the simple logistics of connecting busy professionals. Role become blurred, creating confusion that leaves critical tasks either duplicated or, worse, entirely overlooked. Power struggles simmer beneath the surface of superficially collegial interactions, fuelled by competing mandates, differing theoretical frameworks, and unacknowledged biases about which perspectives should take precedence.
All these challenges unfold against a backdrop of chronically depleted resources – not just financial constraints, but shortages of time, training opportunities, and the emotional bandwidth necessary to engage in thoughtful, creative work with complex cases. If any of this sounds familiar to you, you might find something useful to your practice below.
-
At the foundation of every effective care team sits an agreement among professionals about what they're there to do. This is best informed by a jointly held explanation of how why this client is struggling with this problem at this time. This can be thought about as a shared case formulation, behavioural analysis, or problem conceptualisation – each of these seeks to move beyond a list of problems or diagnoses to a coherent account of what makes the client vulnerable to their problem, what activated their struggles, and how those struggles are maintained. It is not only information gathered about a client, but the meaning made collectively from that information. This creates a working theory the team can test, revise and act upon together.
Without this foundation, even well-resourced teams risk becoming a collection of parallel interventions reacting to symptoms rather than causes. A school might manage disruptive behaviour, a clinician might treat anxiety, a housing worker might pursue stable accommodation – each accurate, none connected. A robust Shared Understanding focuses us toward a different whether every intervention follows from, and contributes to, our collective explanation of what is happening for this client.
How this is formed and creates purpose
No single professional holds a complete view of a client's world. Each discipline observes through a particular lens (e.g. clinical, educational, developmental, relational) and each lens reveals important but incomplete information. Bringing these together requires robust information sharing and the active work of bringing others into our professional language and theoretical models. Ensuring there are opportunities for the voices to be in the room (really or virtual) to have open, focused conversations is critical to achieving this and so is those conversations being led with purpose. Using tools or frameworks that organise information can help professionals collaboratively spot patterns amidst data points and give transparency and accountability to the process and can be 'put up on the wall' (virtual or real) in these meetings.
Like any foundation, Shared Understanding requires ongoing maintenance rather than a one-off assessment. As new information emerges, the team's understanding must be revisited and refreshed. Teams that neglect this risk building competent-looking structures – clear roles, regular meetings – on an explanation of the client's needs that quietly stopped being true some time ago. However, once a team holds a genuine, integrated explanation of how a client's difficulties developed and what sustains them, their purpose follows naturally. Interventions can be selected because they address a hypothesised maintaining factor and priorities can be sequenced according to what the formulation suggests matters most.
Mapping the terrain
A useful metaphor for this process is mapping unfamiliar terrain. Each professional stands at a different vantage point, observing the same landscape from an angle that may be unavailable to their colleagues. Taken alone, any single vantage point risks distorting the importance of the elements in view – triangulating those views can resolve this. By comparing several fixed points of observation, surveyors can locate a single, more accurate position than anyone sighting could produce alone. Care teams achieve this by systematically sharing what each member has observed, then sorting this shared information for pattern and meaning: noticing where accounts converge, where they diverge, and what the divergences themselves might mean.
The result is a dynamic map, a collectively constructed and regularly revised representation of the terrain the team and client are navigating together. This map does not eliminate uncertainty or professional difference; rather, it uses that difference in productive ways by integrating perspectives into a clearer picture and locating where genuine ambiguity remains for further exploration.
With this map in hand, care teams gain a collective basis for planning and action. Decisions about intervention, sequencing and priority can be made in reference to shared terrain rather than isolated viewpoints. Just as an accurate map allows travellers to choose a route with confidence through difficult territory, a well-constructed Shared Understanding allows a care team to navigate complexity with purpose – the essential foundation upon which every other element of the House Model is built.
How Shared Understanding supports the House
In the architectural metaphor of the House Model, Shared Understanding is the base upon which every other structural element rests. Without an accurate, integrated formulation of the client's difficulties, walls of Defined Roles become arbitrary divisions rather than coordinated domains of expertise and Mutual Respect becomes harder to sustain when team members are working from unreconciled explanations of what is happening. Amidst this, Clear Communication has nothing substantive to carry and Change Markers lose meaning, since progress cannot be measured against an underlying formulation.
-
Interprofessional work asks people trained in different disciplines, employed by different organisations, and working to different mandates to hold an integrated understanding of a client that depends on one another. This is a really difficult task. Each profession develops its own vocabulary, priorities, and processes to manage risk. This is further stressed by time pressures that mean information sharing is missed and the emotional weight of the work leading practitioners acting defensively. Left unaddressed, these barriers fragment the very picture care teams exist to hold together. Overcoming them matters because clients – many of whom have already experienced fragmented, contradictory systems including, at times, their own families of origin – depend on the team to model something better: a coordinated response where information is managed responsibly.
Importantly, Clear Communication cannot be confined to scheduled meetings. It is a continuous thread of connection, information-sharing, and mutual support that runs among members of a care team: a phone call flagging a change in risk, a quick message confirming a plan has held, a check-in after a difficult contact. Meetings punctuate this process, but they cannot constitute it. Teams that treat communication as something that only happens in the room lose the timely, informal exchange that lets them respond as client circumstances shift.
Seeing the whole elephant
This challenge is well articulated in an old parable of blindfolded people each introduced to a mystery animal, asked to work out what it is by touch alone. One grabs the trunk and determines it a snake; another the tusk and thinks it a walrus; a third the leg and believes it a hippopotamus. Each is reasonable based on what information they have, and each could be readily convinced their partial experience is the whole truth. If each was asked afterwards to defend their conclusion, conflict would emerge when they present their individual answer to the group.
Care teams face the same challenge. Each practitioner sees a different part of a client's life (e.g. home, school, health, justice, family) and forms a genuine but partial understanding. The parable's resolution is simple: if the blindfolded people described, precisely and without assuming the others already understood, exactly what they had felt, they could jointly work out that they were touching an elephant. Clear Communication is this act of intentional sharing – the deliberate, ongoing process of giving and asking to receive each person's partial picture so the team can assemble something closer to the whole.
Metacommunicating toward a shared language
Each sector carries its own shorthand – clinical terms, legal thresholds, educational or justice-system jargon – that can obscure meaning rather than clarify it. Clear Communication means more than simply avoiding jargon; it means actively translating professional or sector-locked language into terms other team members, and the client, can understand. This invites others into that shared vocabulary rather than assuming they already have it. A practitioner who explains why a term matters, not just what it means, helps the whole team and the client work from common ground.
This means that sometimes we need to talk about how we are talking before we can resolve what is being discussing. This is metacommunication: naming shifts in tone, tension, or disengagement as when they appear, rather than waiting for a breakdown. A simple observation (e.g. “I've noticed we've gone quieter on this topic than usual; what could be happening for us?”) can prevent weeks of misalignment. Used early and routinely, rather than only in crisis, metacommunication keeps small frictions from hardening into entrenched positions.
Making meeting time count
Because meetings remain the team's central integration point, using that time well matters enormously. A clear agenda with a stated purpose, defined topics, and realistic time allocations orients everyone before they arrive and prevents drift into tangents or repetition. Effective chairing brings this into real-time: opening space for quieter voices, gently redirecting those who dominate, naming tensions rather than letting them simmer, and checking time against the agenda throughout. Together, a strong agenda and effective chairing can turn meeting time from a scarce resource into a genuine engine for shared understanding.
Communication as the House's connective tissue
Within the House Model, Clear Communication is what allows Shared Purpose and Defined Roles to actually function under pressure. It is the ongoing exchange in addition to regular meetings that keeps fragmented pieces of a client's story moving toward a coherent whole. Along the way, meta-communication supports Mutual Respect through a team noticing, naming, and repairing its own missteps before they compromise the care it seeks to provide.
-
Role boundaries are the lines a care team draws around what falls inside and outside each professional's domain. Like walls in a house, they create separate rooms while still supporting one shared roof, dividing the work without dividing the team. Done well, boundaries reduce duplication, prevent gaps, and let each practitioner work with confidence within the space of their own expertise. Done poorly, they either fragment care into disconnected silos or dissolve into confusion about who is doing what.
Building transparent boundaries
Defining a role boundary starts with aligning authority and responsibility. Authority is the imbued right to make decisions in a certain domain, such as a medical practitioner’s capacity to prescribe medication or a police officer’s ability to arrest – it is the power or right granted to a person to make decisions, command others, and use resources. Responsibility names which risk and needs belong to which professional or organisation such as a child protection practitioner being accountable to a Magistrate of the Children's Court or the need to account for funds in an NDIS plan by the support coordinator – every practitioner or service carries particular obligations associated with their legislation, funding, and ethical accountability to the client and to the community.
Both of these facets need explicit naming in a care team and space given to clarify where each belongs and how they come into alignment. A practitioner asked to manage a risk without the authority to act on it – approve a placement, access funds, escalate a concern – is set up to fail. Similarly, a professional empowered to make decisions about resource use without any accountability – agree to support hours, endorse service commencement, restrict rights – becomes disconnected from impact and can become careless or capricious.
Navigating blur and breach
Two failure patterns deserve particular attention. The first is the missing role: a need identified but nobody holding responsibility for it, whether because a service was never engaged, a referral stalled, or a gap isn't able to be filled in the current service context. Missing roles can be especially dangerous when they are left unnoticed or unnamed. Teams should routinely and explicitly ask who is responsible for each identified risk and need, and name any gaps as a shared, explicit problem rather than letting them go unnoticed. This allows action to be taken out advocacy to be uplifted.
The second is role duplication: two or more practitioners believing they hold the same responsibility or authority, usually without realising it. This produces competing plans, contradictory messages to the client, and even contests over whose judgement prevails. Left unaddressed, blurred authority over decision-making erodes accountability: when everyone is a little bit responsible, no one is may feel fully responsible, and when something goes wrong, the team cannot meaningfully learn from this and correct moving forward.
Three states of boundary strength
A useful way to calibrate boundary strength is to think of it as water in its three states:
· Gaseous steam boundaries are too diffuse. Practitioners drift beyond their expertise, information floods every channel, and everyone tries to hold everything. This feels inclusive, but a team spread across all the available space has no shape and little impact – nobody's specific expertise, decisions, or accountability remain identifiable.
· Solid ice boundaries are too rigid. Practitioners retreat to strict definitions of their role, defaulting toa “That's not my job!” mentality. This preserves a clear shape but at the cost of connection and impact – the team loses the flexibility to respond to a client's actual, changing context, and needs that fall between defined roles go unmet.
· Flood water boundaries hold the balance. Each practitioner maintains a clear, defined space of responsibility and authority, while retaining enough flexibility to flow toward needs that fall between roles when the situation calls for it – always naming these temporary crossings openly rather than letting them become permanent confusion.
Supporting the House
As a wall within the House Model, well-calibrated Role Boundaries share the weight of risk and need down to the foundation of Shared Purpose, without collapsing into either rigidity or diffusion. When boundaries hold this flexible balance – authoritative and responsive – clients experience a team that is both dependable and genuinely able to meet them where they are.
-
Mutual respect is what allows a care team to tolerate difference without fracturing. When it's working, professionals speak about colleagues with dignity with their client even when there's been a rupture in their relationship; professional disagreements can be aired as differences of assessment rather than character attacks; and practitioners treat “I don't know” as a flag to move in with curiosity rather than a weakness. What's more, all the time this respect is visible to the client: professionals who model it aren't just being polite, they're showing the client what a trustworthy relationship can look like.
How parallel process erodes respect
Complex work rarely spares the team who delivers it. As set out in The Outer Layer, care teams often unconsciously mirror the very dynamics of the clients they support. Left unaddressed, this parallel process is one of the most corrosive forces acting on mutual respect.
Siloed work is a common experience – a client whose trauma has taught them to trust no one can leave a team quietly retreating behind increasingly rigid role boundaries, sharing less, and assuming the worst about colleagues they no longer directly speak to. Avoidance shows a similar face – difficult conversations that may risk disagreement are put off, meetings become polite but superficial, and unresolved tension becomes relational distance. Control battles emerge when anxiety about a case tips into contests over whose understanding of the client’s need is “right”, with professionals unconsciously replicating a client's own experience of powerlessness or chaos by fighting for authority rather than collaborating.
Left unnamed, these patterns become self-reinforcing, and teams stop talking directly to one another, start talking more about one another, and mutual respect quietly erodes.
Building respect back in
Reversing this drift is possibly by consistently walking a simple path: talk, behave, and even try to think about colleagues – whether they're in the room or not – in ways you'd be comfortable them hearing. This extends into how the team behaves in front of clients. When a client raises a grievance about a specific team member, the most respectful and useful response is usually to support the client to raise it directly with that person, rather than absorbing or relaying the complaint on their behalf. This resists the pull toward triangulation and gives the client a direct experience of a professional relationship that can hold disagreement without collapsing.
The same principle applies to repair. When a client's relationship with one team member ruptures, an intact, trusted relationship elsewhere in the team can be intentionally leveraged to support reconnection by helping the client find the words and safety to re-engage directly. This can be a therapeutic use of parallel process: rather than the team's fractures mirroring the client's, the team's capacity for respectful repair becomes something the client can borrow and, over time, internalise.
Kintsugi: strength through repair
The Japanese art of Kintsugi offers a useful metaphor for this work. I'm Kintsugi, broken pottery is mended with lacquer and powdered gold; the cracks aren't hidden but illuminated, and the repaired piece is considered more valuable than the original, unbroken one. Rupture in a care team whether because of a sharp disagreement, a missed handover, a moment of defensiveness doesn't need to be treated as damage to be concealed. When named and then repaired with curiosity, it becomes gold-threaded evidence that the relationship can withstand pressure and hold complexity. Teams that repair well don't return to where they started; they become more resilient, more able to tolerate the next disagreement and use it productively for their client.
Mutual Respect and the House Model
Within the House Model, mutual respect is the reinforcement that prevents complex pressure on the roof from coming down the walls and foundation beneath it. It is built and rebuilt one respectful conversation, one direct conversation, one repaired rupture at a time. When it holds, teams offer clients something rarer than any single service: a living demonstration that relationships can be honest, imperfect, and safe all at once.
-
An effective Change Marker is specific and observable, not a vibe, impression, or hunch. It's a behaviour or event that client, family, and team have agreed in advance will count as evidence of progress. “Improved engagement” does not work as a marker but “attends three consecutive school days” is. “Better emotional regulation” is not a marker though “uses the agreed calming strategy before escalating, on at least two occasions this week” is. A good marker is concrete enough that two care team members can independently agree on whether it happened. It carries a timeframe helping frame not just what should change, but by when which gives the team will do together if it hasn't.
To be most effective, markers must be co-created with the client, not handed down. Clients navigating trauma, disability, or repeated service involvement, especially where those services are capable of or have demonstrated legislated coercive powers often learn to tell professionals what they want to hear. They can lose sight of what change would mean for them personally and rather focus primarily on case closure. Asking directly how the client would know things had changed meaningfully for them explicitly empowers them as the authority on their own experience and produces markers with far greater motivational weight.
Disrupting drift and avoiding crises driving
Care teams under high pressure are vulnerable to becoming diverted from their goals. This can occur because of a pattern of drift in which the goals become obscured by needs which feels to large to manage or system barriers that are too challenging to overcome – in this circumstance, a care team can begin to drift in an aimless way, maintaining the superficial indicators of collaboration (e.g. attending meetings, giving 'updates', talking positively about one another) without any defined action being taken. There is a parallel in this to overly diffuse boundaries, large volumes of low-impact communication, and a too general and inclusive understanding of the client. Here, change markers can be focusing for a group to attend to small-scale outcomes which can be clearly and objectively achieved or blocked. When the latter occurs, there becomes an imperative on discussing why and how to adjust, leading to further purposeful action.
Another way that care teams can become overwhelmed by pressure is when the frequency and intensity of crises for the client is so great that the system becomes reactively focused. In these circumstances, any longer-term goals are deprioritised repeatedly in favour of 'putting out fires'. There is a parallel here to overly rigid boundaries, overtly harsh communication, and a fractured understanding which lacks the bigger picture. Here, Change Markers help set an intentional balance between responding thoughtfully to emerging needs while also attending to large-scale growth or improvement which can alleviate the factors that generate crises.
Sometimes, in ways that can parallel client’s own struggles, a care team will oscillate between these two positions, feeling like they're caught in a whirlpool of inaction. In any case, the markers being explicit and time-bound works to reorient a care team to meaningful change and the barriers (potentially identifiable in other elements of the House) that are blocking this. Because they specify what should be observed and by when, drift becomes visible – a marker not achieved at its expected date is a fact the team must reckon with, not a discussion item to be rolled over. This creates a structured, blame-free moment for reflection on what got in the way, whether a marker still fits, and in what ways the plan needs to adapt. Because markers are anchored in Shared Purpose, they also hold a legitimate claim on attention even during crises, giving the team impetus to return to the non-urgent, longer-term goals rather than letting them repeatedly fade behind the latest emergency.
Markers as anchors
It helps to think of Change Markers as anchors rather than a finish line. An anchor doesn't fix a boat rigidly in place as it allows the necessary bobbing and adjusting to accommodate the moving water – but it does let the crew feel, through tension in the line, the exact moment the boat has drifted off course. Without an anchor, drift is invisible until you look up and find yourself a long way from where you intended. With one, that moment of tension becomes a decision point that allows us to correct by posting out more line if circumstances genuinely require it or reset the anchor if the client's situation has changed enough that the original marker no longer fits. This is the discipline Change Markers bring to the House Model. They demand any departure from course be noticed, named, and chosen deliberately, by team and client together, rather than happening by accretion while everyone is absorbed in the next crisis.
How this strut supports the House
Collaboratively developed Change Markers draw directly on the foundation of Shared Understanding as, without it, markers risk being co-opted by distractions. The walls of Defined Roles give markers their accountability as each indicator sits clearly within someone's responsibility, preventing diffusion of ownership. Clear Communication is what keeps markers active between meetings, sharing unexpected roadblocks to progress. While, at meetings Mutual Respect makes it safe to report lacking progress forthrightly, believing it will be treated as information to be curious about together. Change Markers function as the anchor points that keep the whole structure oriented, particularly once the roof of case complexity bears down.
-
Throughout this guide, we have worked through how Shared Purpose, Defined Roles, and Clear Communication provide the foundation, walls, and connective tissue of collaborative care, reinforced by Mutual Respect and Change Markers. Together, these elements create a structure capable of holding real-world complexity while supporting durable, meaningful change. But it can be hard to see things that have degraded or slipped out of place when you're living amidst them for long periods or when there are loud distractions around.
When this happens, a care team becomes susceptible to parallel processes taking over. As clients' fragmented, distressed, or overwhelmed internal states seep into the care system, they can settle into the very rooms we have built to support change and muddy roles, corrode communication, and undermine the respect that holds care together. At these times, even our values driven practice can reach a limit.
A team fully committed to shared purpose, individually reflective and mutually respectful, can still find itself caught inside a pattern it cannot see – precisely because the issue has crept inside. In these moments, the House needs something beyond its own walls: an outer layer, invited in as a critical, reflective friend. A senior practice or clinical professional, drawn from one of the involved organisations but positioned outside the day-to-day system, can offer what the team structurally cannot generate for itself. When it seems like we've confirmed the elements of our structure and things still aren't working, it can be helpful to ask for this external inspection.
We can think about this as our care team being dancers on a crowded floor, all absorbed in the music, their client, their own footwork. Even skilled dancers on the dancefloor can't see the way their collective movement comes together into patterns: circling the same point, colliding, or drifting apart. Equally, someone watching from a balcony doesn't see the individual steps, but can see how they form a pattern: where energy clusters, where the dancers split apart, where the dance has gotten stuck. A consultant to a care team occupies that balcony. Not choreographing the dance, but able to see its shape and reflect this back to those still moving within it.
A well-built House won't always eliminate the need for someone up on this vantage point – it will make the invitation easier to extend, and the reflection easier to receive.